




Esketamine and Arketamine: Chemistry Matters — But So Does Delivery
Not all ketamine is the same. Chemically, ketamine comes in two mirror-image forms — S-ketamine and R-ketamine — that behave differently in the brain. And not all delivery methods are created equal. Some offer fast, precise absorption; others involve more variability.
What Are the Types of Ketamine?
Ketamine comes in three main forms used in medical settings, and they differ in chemistry, regulatory status, and how they’re delivered:
- Racemic ketamine
- S-ketamine (esketamine, the active ingredient in Spravato)
- R-ketamine
The differences between these three types of ketamine matter clinically because each behaves differently in the brain and is delivered via different routes — which directly affects dosing precision, insurance coverage, and which conditions each is approved or used to treat.
To make informed choices about treatment, it’s helpful to understand both:
- The stereochemistry (shape & structure) of ketamine
- The routes of administration that affect how well the medication works in your body
This article explains what makes S-ketamine more active, why bioavailability matters, and how these two factors converge in treatment design.
S-Ketamine as the Active Component
Ketamine, as commonly used in clinics, is a racemic mixture — a 50/50 blend of two mirror-image molecules: S-ketamine and R-ketamine.[1]
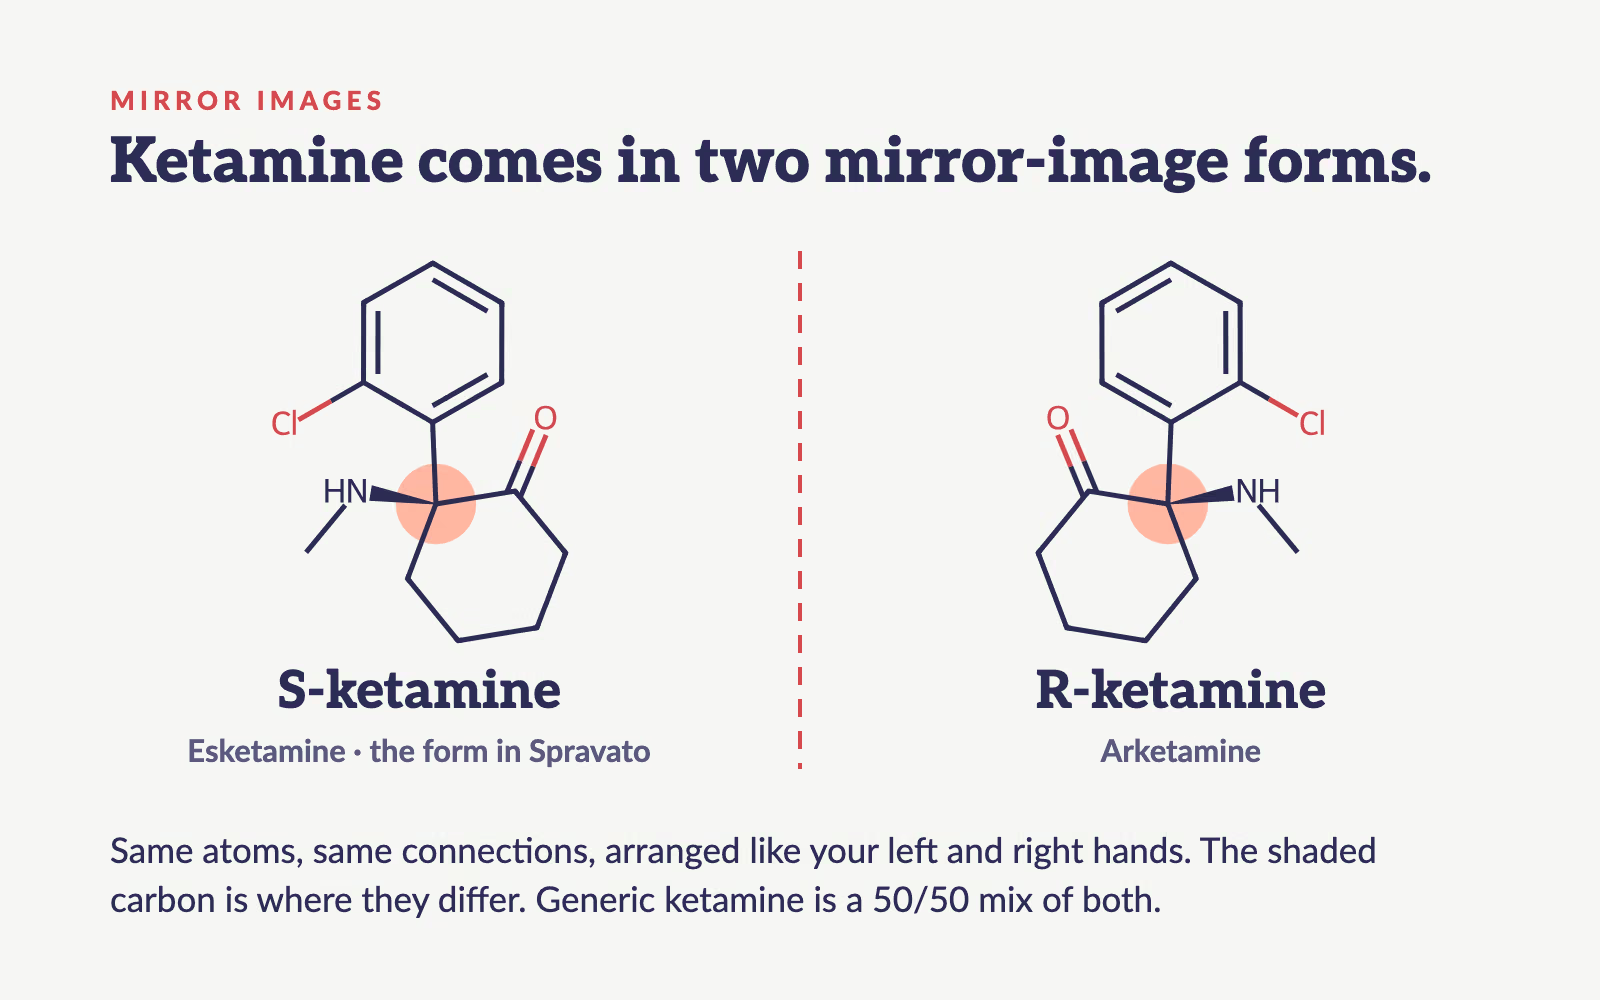
Among these, S-ketamine is considered the more active component in the treatment of depression.[1] It has:
- Greater affinity for the NMDA receptor[2]
- More potent glutamate modulation
“S-ketamine is what’s doing the heavy lifting when it comes to blocking the NMDA receptor and initiating downstream changes.” — Dr. Ben Yudkoff
This is the form isolated and used in esketamine (Spravato), the FDA-approved intranasal therapy for treatment-resistant depression.[3]
R-Ketamine: Less Active at the NMDA Receptor
While R-ketamine still binds to NMDA receptors, it does so with less potency and requires higher concentrations to achieve therapeutic effects.[1] According to Dr. Yudkoff and broader clinical consensus:
- R-ketamine has lower clinical activity
- It may play a supportive role in racemic mixtures
- But it’s not clear if R-ketamine is necessary for the antidepressant effect to occur
That said, some early research — so far mostly in animal studies — suggests R-ketamine may have longer-lasting antidepressant effects and anti-inflammatory properties.[2][4] These areas remain under investigation, but for now, the clinical guidance is clear: S-ketamine drives the core therapeutic effect.
“We think of R as more inert, at least for now. That could change with new data, but in practice, it’s S-ketamine we’re relying on.” — Dr. Ben Yudkoff
Where R-ketamine research stands now. R-ketamine (also called arketamine) was set aside early because it is less potent at the NMDA receptor, though it appears to act through other pathways.[1,10] Early animal research also suggests it may cause less dissociation.[9] Speaking to families in October 2026, Dr. Yudkoff noted that research groups in Australia and Europe are studying its antidepressant effects with promising early results, while US trials are at earlier stages. It is not FDA-approved, and how it compares with racemic ketamine and esketamine is still being worked out.
Practical Implications: Ketamine Route and Formulation Matter
While chemical differences matter, how the medication gets into the body plays a crucial role in whether it works effectively. This is where the conversation shifts to bioavailability — the percentage of a drug that reaches systemic circulation in an active form.
Direct Bloodstream Routes: IV and IM Ketamine
Intravenous (IV) delivery has 100% bioavailability by definition, and intramuscular (IM) injection comes close — about 93% in a classic human study — because the medication is absorbed directly into the bloodstream instead of being broken down by the liver first.[5] These methods:
- Deliver consistent, predictable dosing
- Allow flexible titration for rapid symptom changes
- Are commonly used in off-label ketamine clinics
“IV and IM are where we see the most dosing precision. When timing and intensity matter, those routes are often preferred.” — Dr. Ben Yudkoff
Racemic Ketamine: More Variability
Intranasal and transbuccal forms of racemic ketamine (used off-label) have lower and less predictable bioavailability — roughly 30% to 50% in pharmacokinetic studies:[6]
- A portion of transbuccal ketamine is often swallowed, and swallowed ketamine is largely broken down before it reaches circulation, reducing the overall amount that gets into the blood stream[5]
- Intranasal delivery (which requires higher volumes) can sometimes result in small leakages and swallowed ketamine with the same issues as transbuccal ketamine[7]
These factors can lead to inconsistent results in some cases — especially when patients are not monitored or formulations are not optimized.
S-Ketamine Nasal Spray (aka esketamine or “Spravato”): Engineered for Fidelity
Spravato, by contrast, delivers S-ketamine in a standardized nasal spray with a well-characterized absorption profile: about half of each dose reaches the bloodstream, consistently across doses.[8]
“It’s not just about esketamine being the right molecule. It’s that Spravato delivers it in a way that’s repeatable — and that matters for insurance, monitoring, and safety.” — Dr. Ben Yudkoff
This route may not be superior in effect, but it delivers a standardized, repeatable dose. It is often more accessible and covered by insurance when prescribed through a REMS-certified clinic.
When it comes to ketamine therapy, structure and delivery matter. At Lumin Health, we help patients and families make sense of these differences — not to complicate, but to clarify. Because when you understand what’s happening biologically and logistically, it’s easier to make a treatment plan that fits your goals, your access, and your life.
What this means for your ketamine treatment plan
For most people considering treatment, the S-vs-R isomer chemistry matters less than which delivery route their insurance covers. FDA-approved Spravato uses the S-enantiomer (esketamine) in a nasal spray, administered on-site under REMS-certified monitoring; it is covered by most major US insurers including Aetna, Blue Cross Blue Shield, Cigna, UnitedHealthcare, Medicare, and ~18 carriers at Lumin Health, with an average patient out-of-pocket cost of $10-$25 per session. Racemic ketamine (both isomers) is delivered intramuscularly at Lumin Health and is typically self-pay. At Lumin Health, ~95% of patients are covered by insurance for esketamine (Spravato). If you're trying to understand whether the isomer chemistry affects your specific plan, the fastest path is our free 30-second coverage checker or to book a free consultation below.
Source: Janssen, Spravato Patient Information — https://www.janssenwithme.com/spravato/
References
- Jelen LA, Young AH, Stone JM. Ketamine: A tale of two enantiomers. J Psychopharmacol. 2021;35(2):109-123. PubMed
- Hashimoto K. Rapid-acting antidepressant ketamine, its metabolites and other candidates: A historical overview and future perspective. Psychiatry Clin Neurosci. 2019;73(10):613-627. PubMed
- Nikayin S, Murphy E, Krystal JH, et al. Long-term safety of ketamine and esketamine in treatment of depression. Expert Opin Drug Saf. 2022;21(6):777-787. PubMed
- Liu G, Ma L, Sakamoto A, et al. Splenic γδ T cells mediate antidepressant and prophylactic actions of arketamine in lipopolysaccharide-induced depression in mice. Pharmacol Biochem Behav. 2024;245:173906. PubMed
- Clements JA, Nimmo WS, Grant IS. Bioavailability, pharmacokinetics, and analgesic activity of ketamine in humans. J Pharm Sci. 1982;71(5):539-42. PubMed
- Yanagihara Y, Ohtani M, Kariya S, et al. Plasma concentration profiles of ketamine and norketamine after administration of various ketamine preparations to healthy Japanese volunteers. Biopharm Drug Dispos. 2003;24(1):37-43. PubMed
- Malinovsky JM, Servin F, Cozian A, et al. Ketamine and norketamine plasma concentrations after i.v., nasal and rectal administration in children. Br J Anaesth. 1996;77(2):203-7. PubMed
- Perez-Ruixo C, Rossenu S, Zannikos P, et al. Population Pharmacokinetics of Esketamine Nasal Spray and its Metabolite Noresketamine in Healthy Subjects and Patients with Treatment-Resistant Depression. Clin Pharmacokinet. 2021;60(4):501-516. PubMed
- Yang C, Shirayama Y, Zhang JC, et al. R-ketamine: a rapid-onset and sustained antidepressant without psychotomimetic side effects. Transl Psychiatry. 2015;5(9):e632. PubMed
- Wei Y, Chang L, Hashimoto K. Molecular mechanisms underlying the antidepressant actions of arketamine: beyond the NMDA receptor. Mol Psychiatry. 2022;27(1):559-573. PubMed
Take the first step today.
If you or a loved one in Massachusetts and the greater Washington DC/Maryland area is struggling with depression or anxiety, Lumin Health's team of experts is ready to help. Book a free 20-minute consultation to learn if ketamine therapy could be the breakthrough you've been looking for.
Available in Massachusetts and the greater Washington DC/Maryland area.
Frequently Asked Questions
What are the different types of ketamine?
Three forms come up in medical care: racemic ketamine, a 50/50 mix of S-ketamine and R-ketamine used off-label; esketamine (S-ketamine), the active ingredient in Spravato; and R-ketamine, also called arketamine, which is still being studied. Esketamine (Spravato) is FDA-approved for adults with treatment-resistant depression and major depression with suicidal thoughts.
What is the difference between S-ketamine and R-ketamine?
They are mirror-image forms of the same molecule. S-ketamine binds the brain's NMDA receptor more strongly and is considered the more active component for depression.
Is R-ketamine used to treat depression?
Not in routine care yet. Some early research, mostly in animal studies, suggests R-ketamine may have anti-inflammatory or longer-lasting effects, but it remains investigational. In clinical practice today, S-ketamine is understood to drive the core antidepressant effect.
Does the way ketamine is given change how well it is absorbed?
The route changes how much medicine reaches your bloodstream, which is called bioavailability. Intramuscular (IM) injection delivers about 93%, so dosing is predictable. Lozenges and some nasal forms of racemic ketamine absorb less reliably, because part of the dose is swallowed and broken down.
Why does Spravato use only esketamine?
Spravato isolates the more active S-form and delivers it in a standardized nasal spray with a well-characterized absorption profile. That makes each dose more repeatable, which matters for monitoring, safety and insurance coverage. It is given on-site in REMS-certified practices, where you are monitored after every dose.





